Stomach Cancer
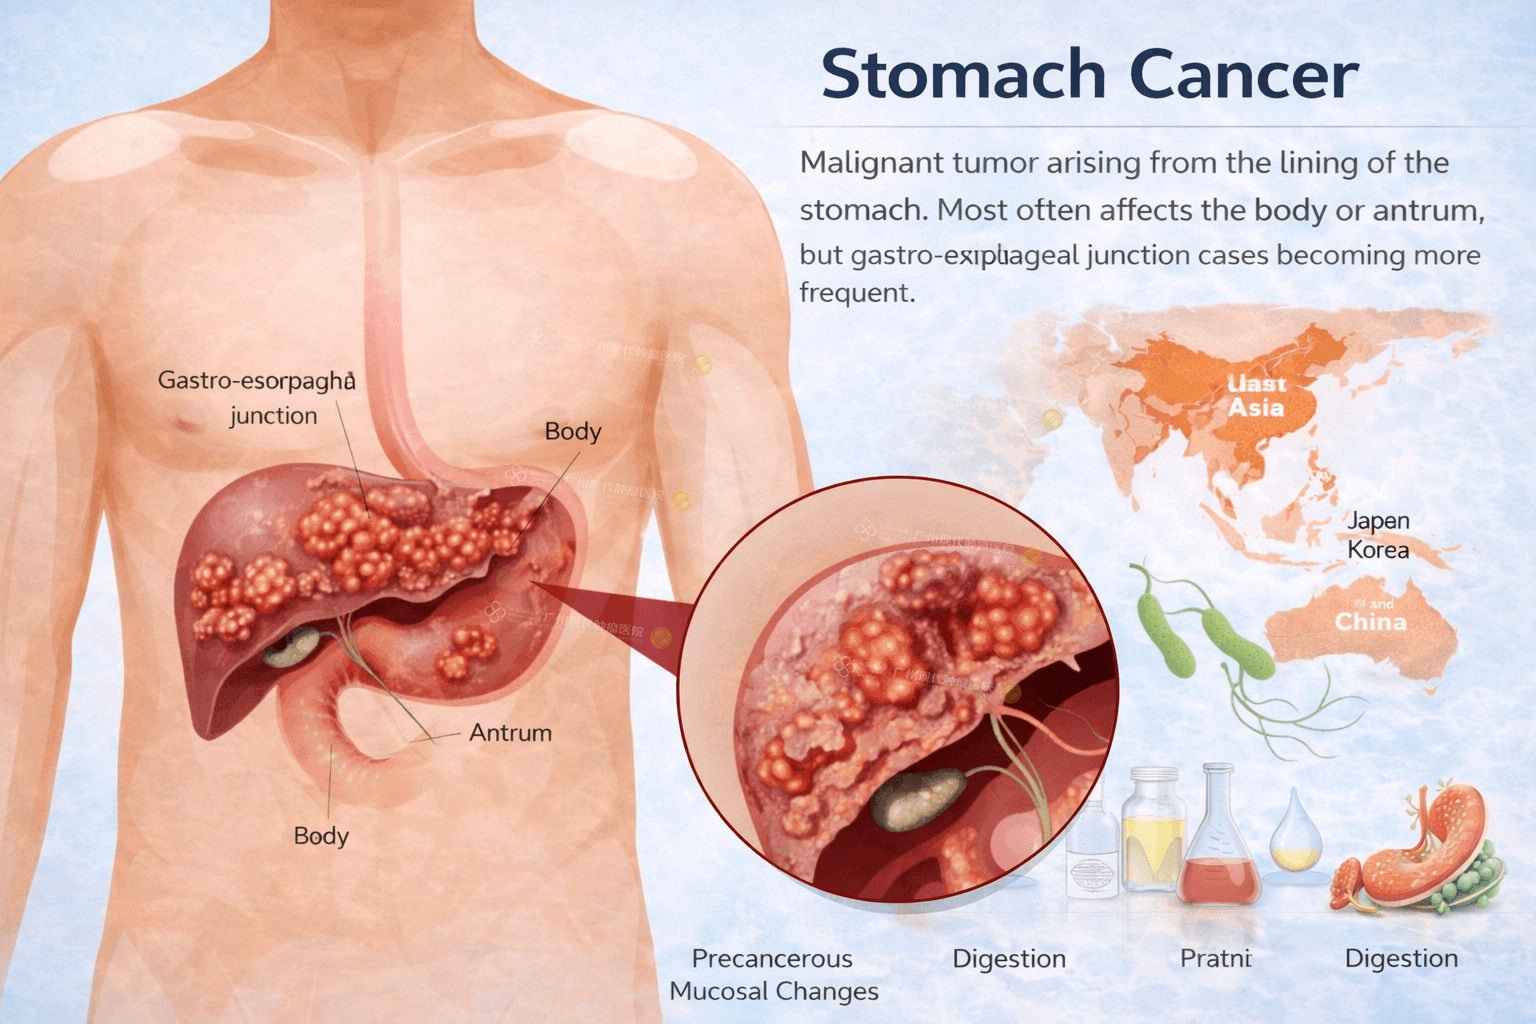
Stomach cancer, also known asgastric cancer, is a malignant tumor that arises from the lining of the stomach. Most stomach cancers develop slowly over many years, often beginning as precancerous changes in the gastric mucosa before progressing into invasive cancer.
The stomach is a hollow muscular organ located in the upper abdomen that plays a critical role in digestion. Cancer can develop in any part of the stomach, but it most commonly affects thebody and antrum. In recent years, cancers near thegastro-esophageal junctionhave become more common.
Despite declining incidence globally, stomach cancer remains amajor cause of cancer-related mortality, especially in East Asia, including Japan, Korea, and China.
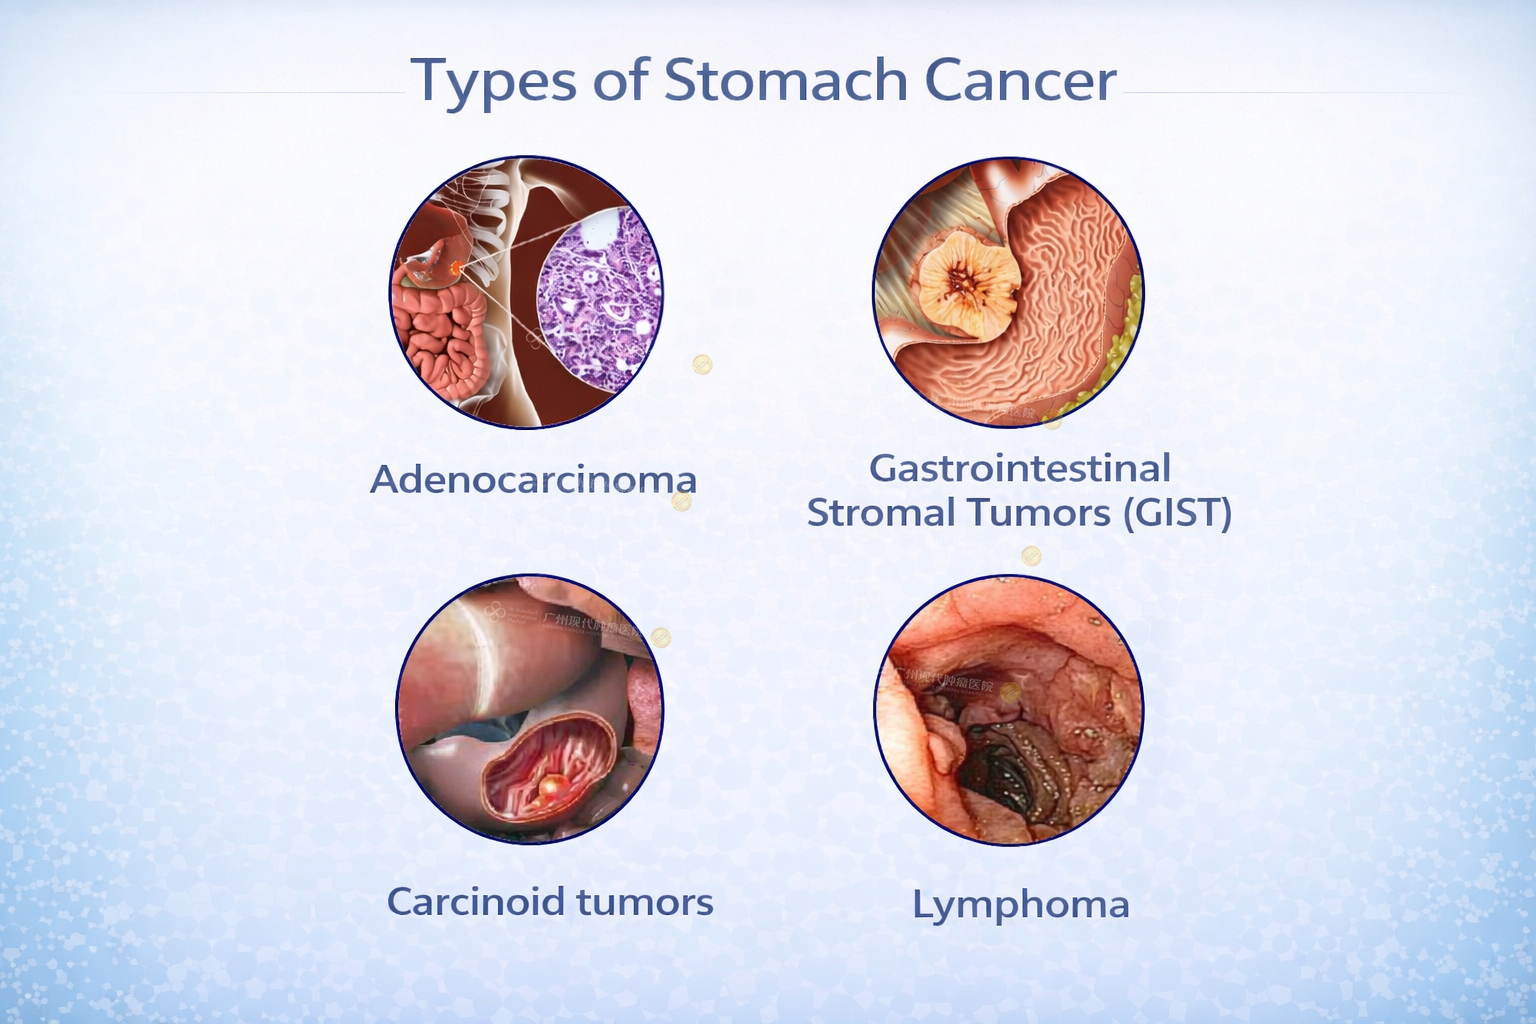

TypesStomach cancer is classified based on histology and growth pattern:
1. Adenocarcinoma (≈90–95%)
The most common type, originating from gland-forming epithelial cells of the stomach lining.
Intestinal type
Diffuse type
Poorly differentiated
Includessignet-ring cell carcinoma
More aggressive, affects younger patients
Leads to rigid stomach wall (linitis plastica)
2. Gastrointestinal Stromal Tumors (GIST)
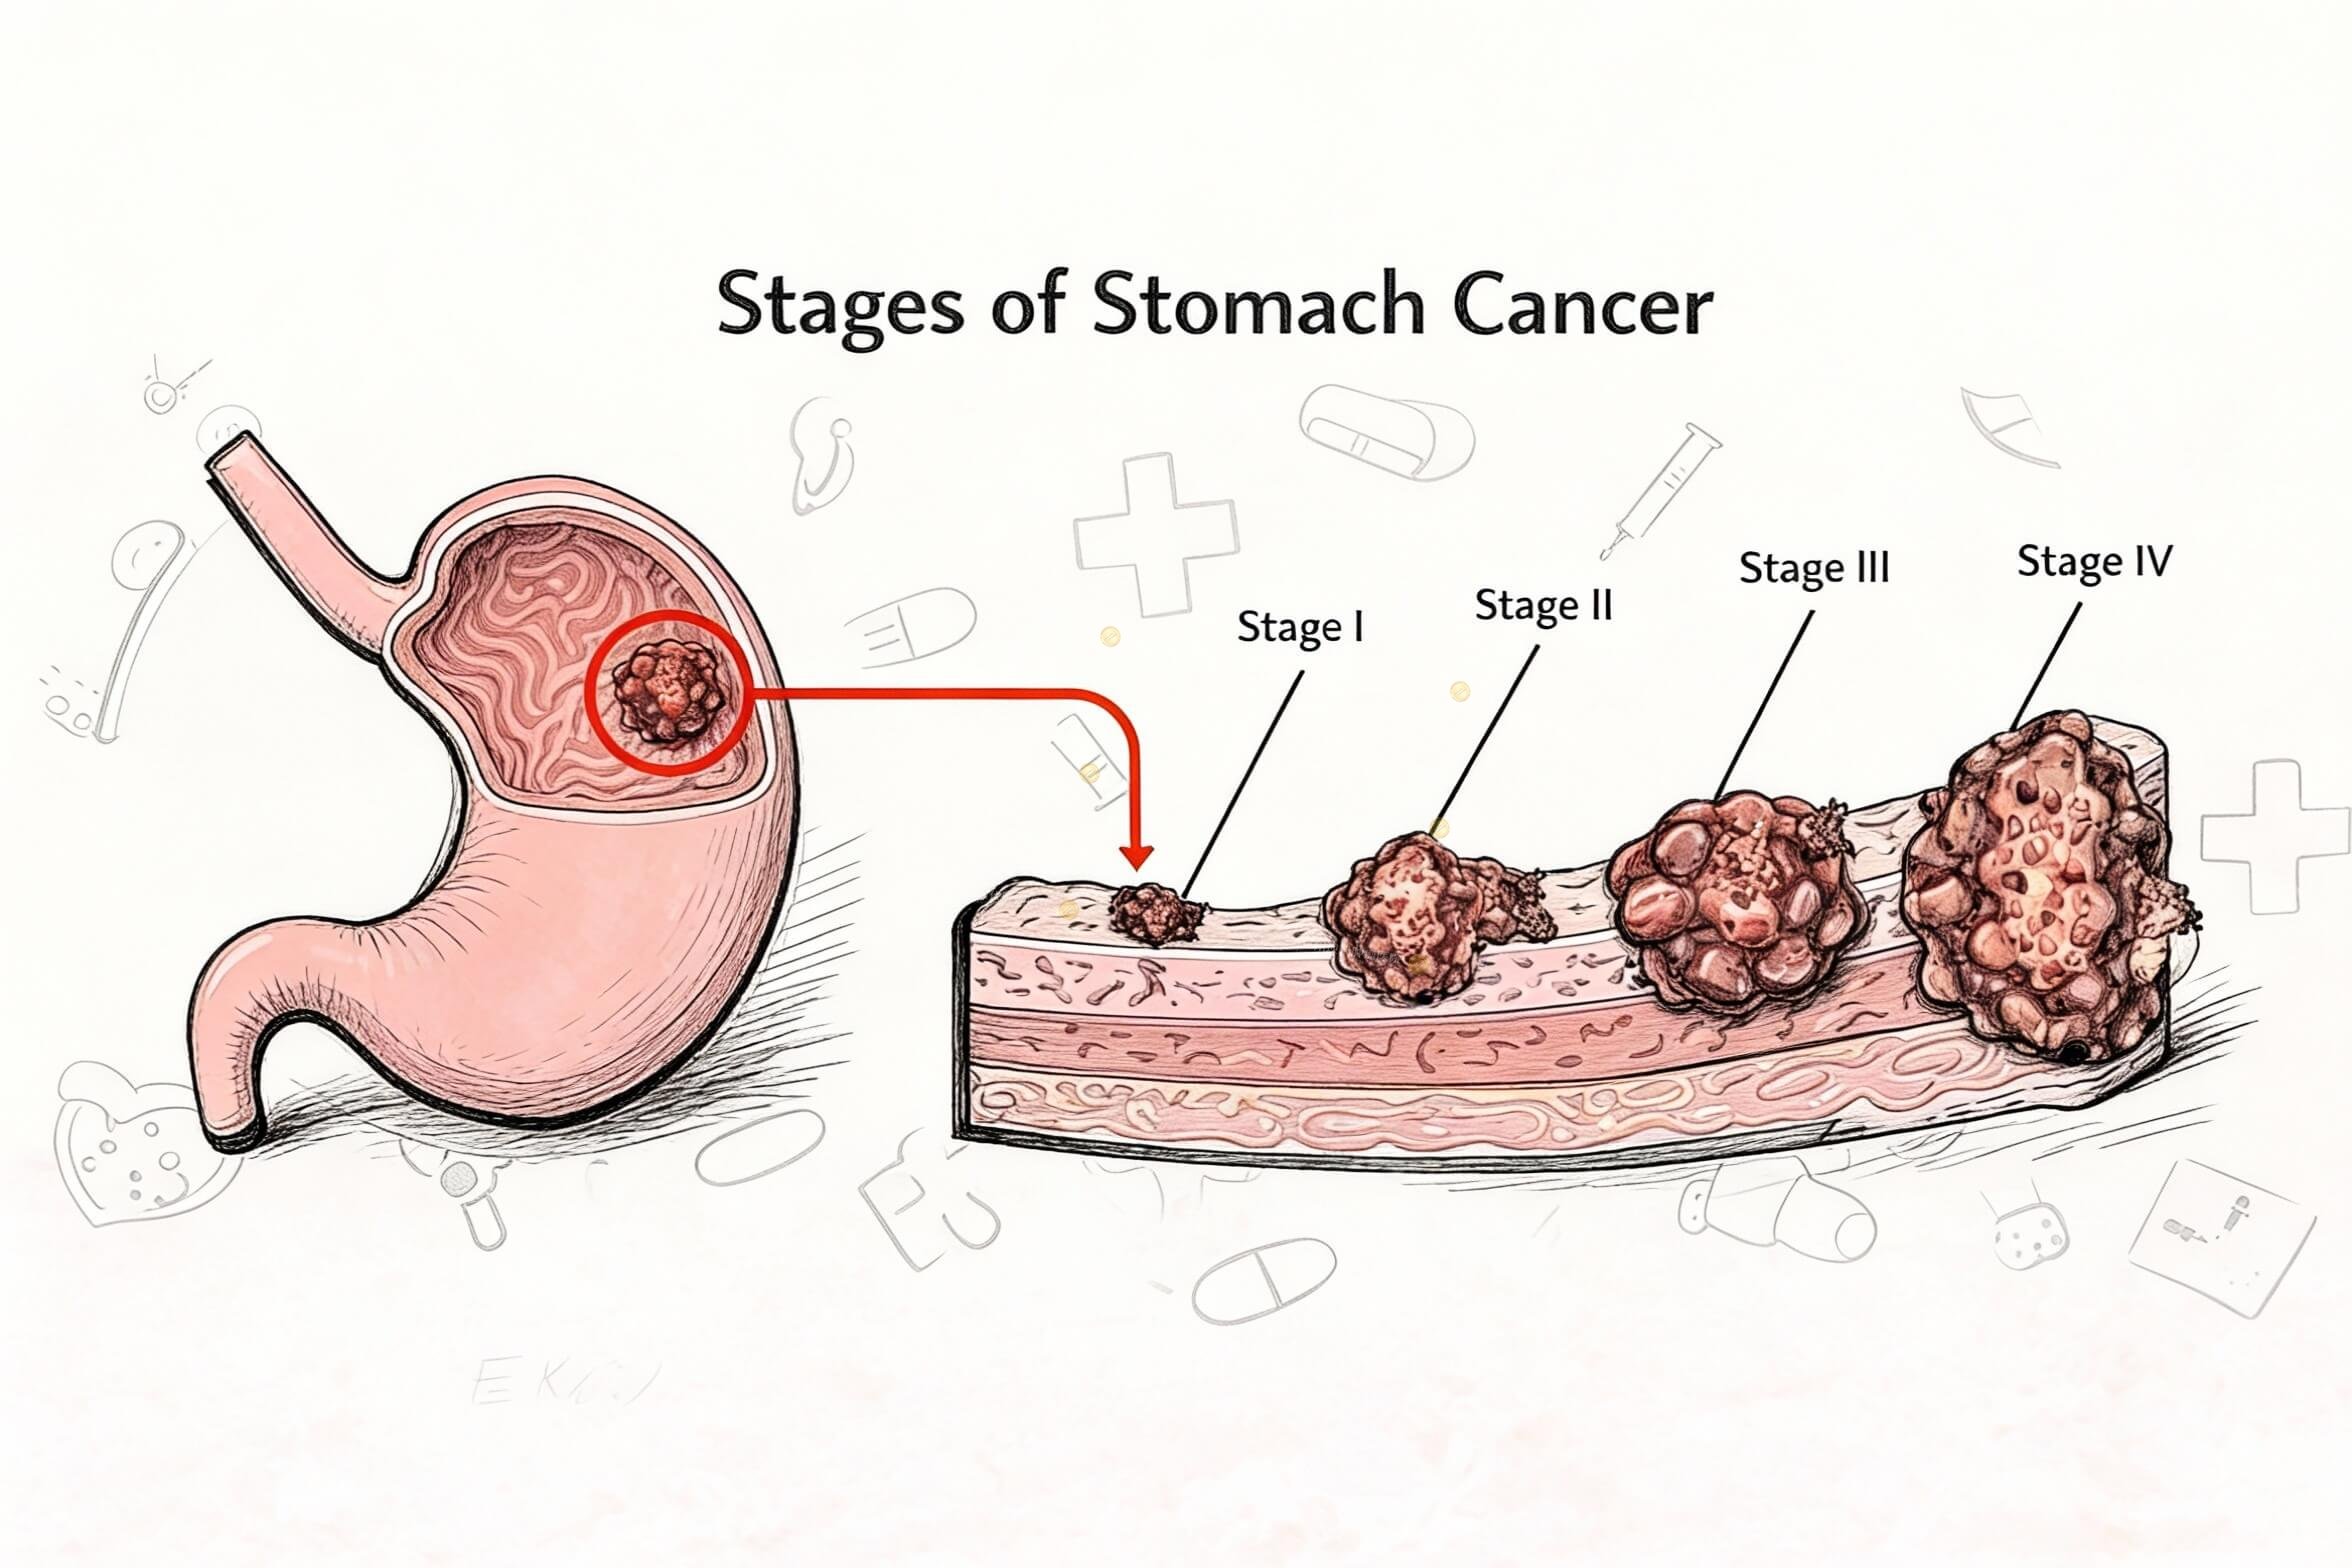
Staging follows theTNM system:
T (Tumor depth)– how deeply the cancer invades the stomach wall
N (Nodes)– lymph node involvement
M (Metastasis)– spread to distant organs
Stage 0: Carcinoma in situ
Stage I: Tumor confined to stomach wall
Stage II–III: Deeper invasion with lymph node spread
Stage IV: Distant metastasis (liver, peritoneum, lung)
Early-stage disease has a much better prognosis, but many patients present at advanced stages due to vague early symptoms.
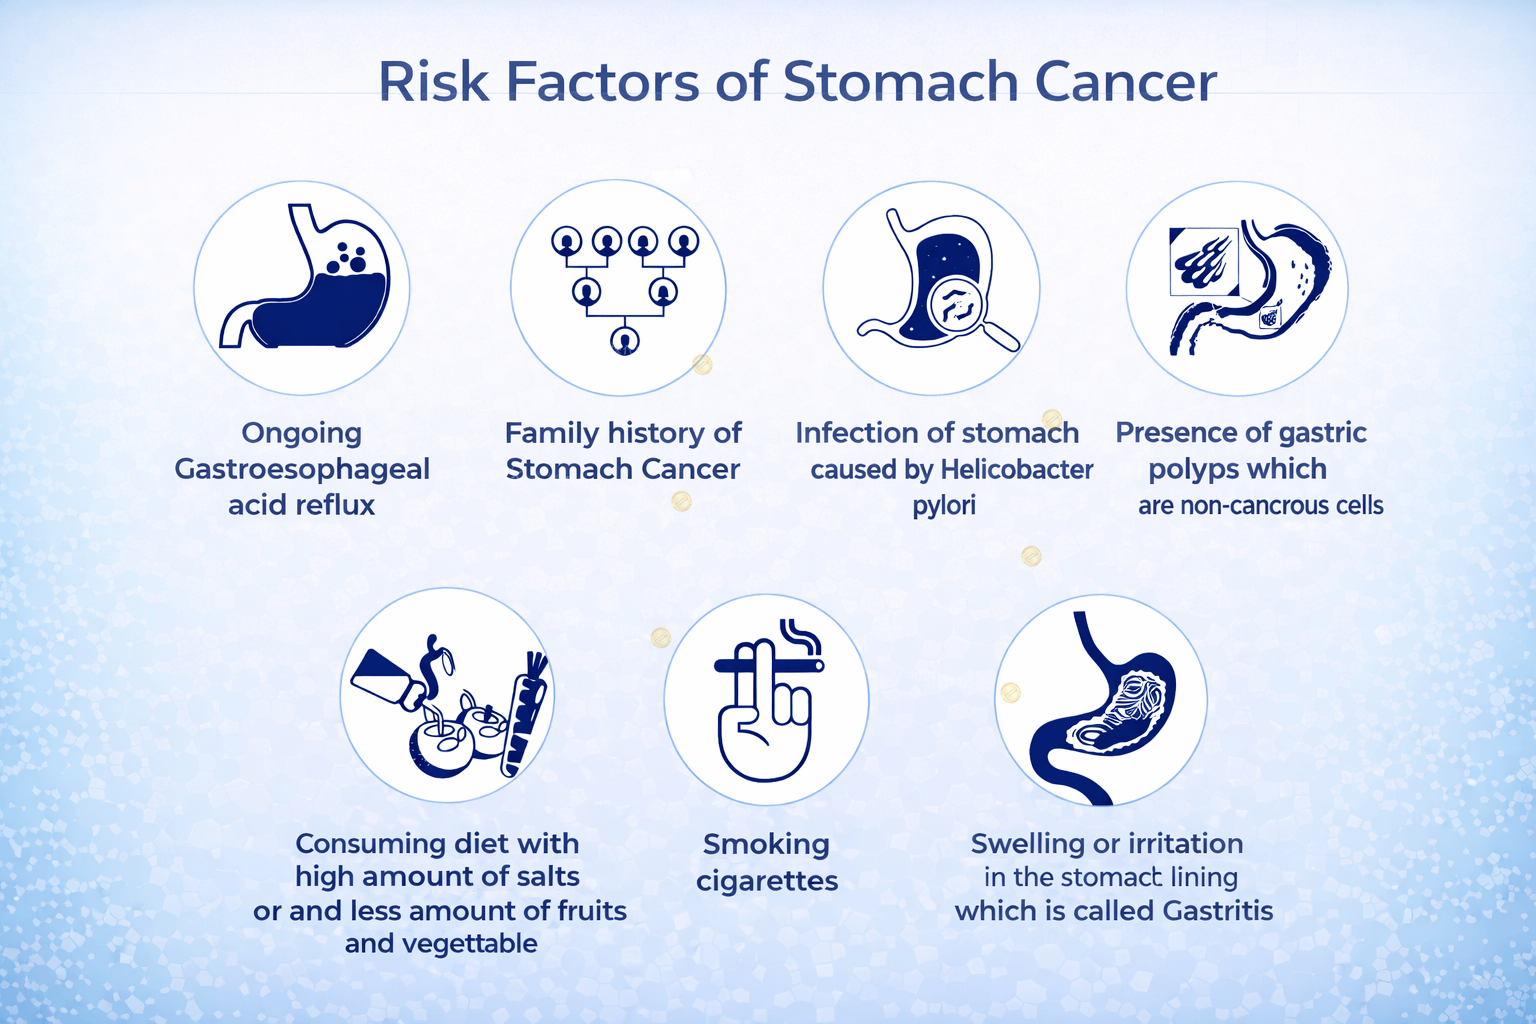
Major risk factors include:
Helicobacter pyloriinfection
Chronic atrophic gastritis
Intestinal metaplasia
Smoking
High-salt and smoked foods
Low fruit and vegetable intake
Family history of gastric cancer
Genetic syndromes (e.g. CDH1 mutation)
Previous gastric surgery
Pernicious anemia
Male gender
Age > 50 years

Persistent upper abdominal pain
Unintentional weight loss
Loss of appetite
Vomiting
Gastrointestinal bleeding (melena or hematemesis)
Iron-deficiency anemia
Dysphagia (if near gastro-esophageal junction)
Ascites in late disease
Symptoms are often nonspecific, leading to delayed diagnosis.
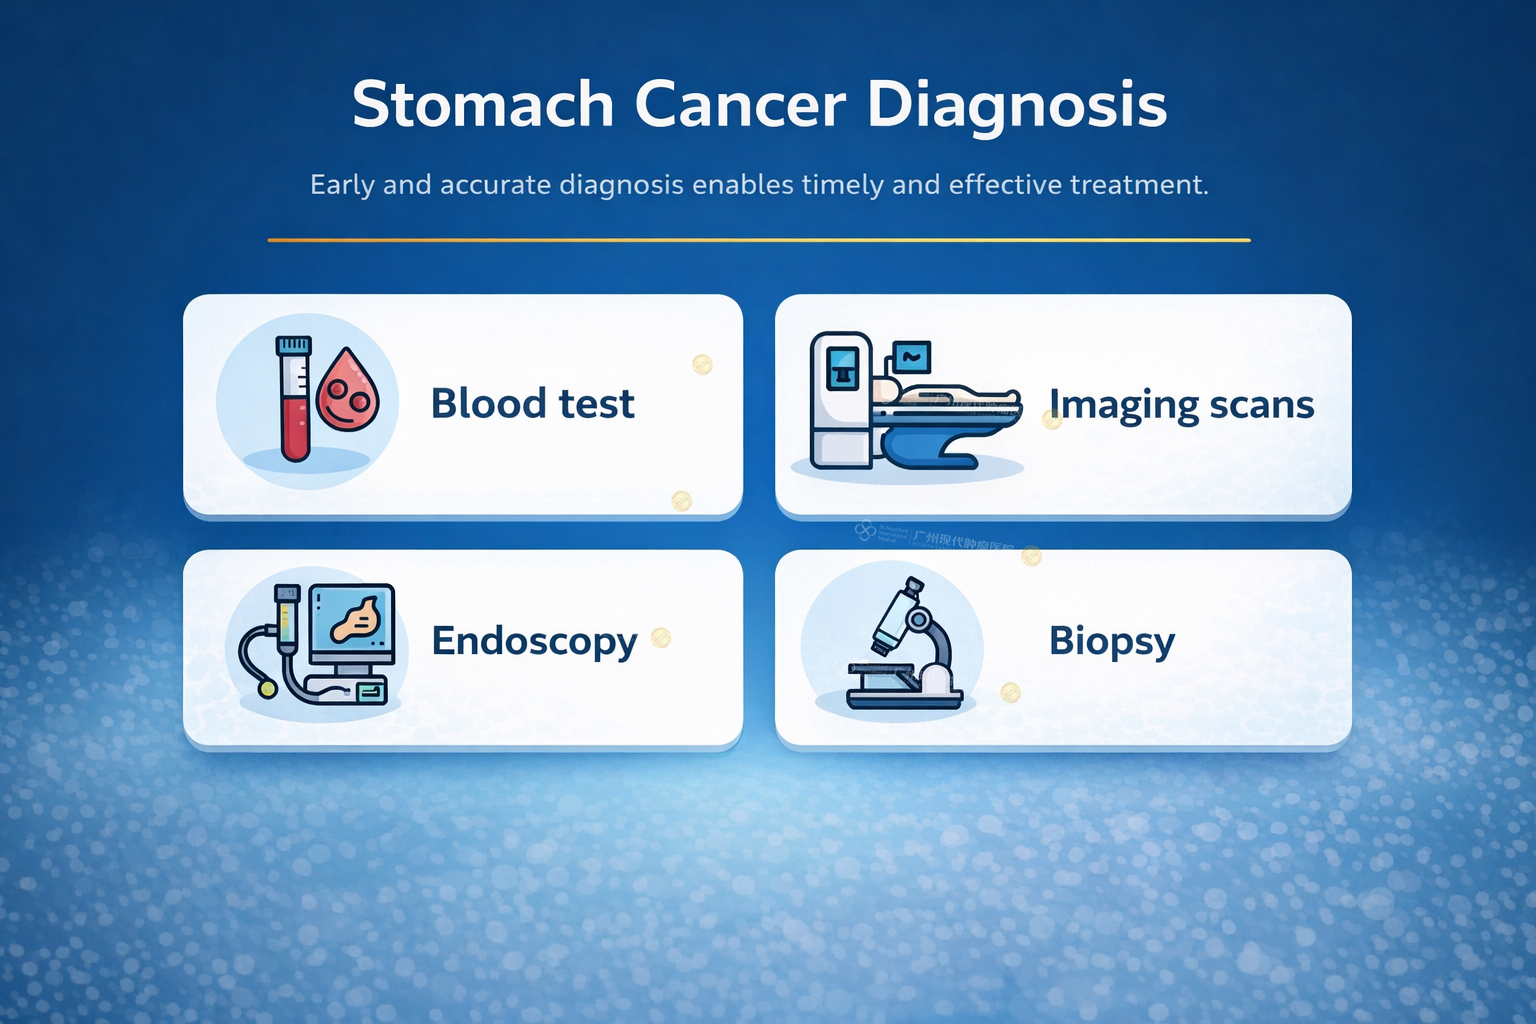
Early-stage (often subtle or absent)
1. Upper Gastrointestinal Endoscopy
2. Biopsy & Histopathology
Q1: Is stomach cancer curable?
Yes, if detected early and treated appropriately.
Q2: CanH. pylorieradication prevent stomach cancer?
Yes, treatment significantly reduces risk.
Q3: Is stomach cancer hereditary?
Most cases are sporadic, but some genetic syndromes increase risk.
Q4: Does diet matter?
Yes. High salt, smoked foods increase risk, while fruits and vegetables are protective.
Q5: Why is stomach cancer often detected late?
Early symptoms are vague and easily ignored.